7-OH Withdrawal Timeline: What It Is and Why Stopping Is Hard
Last updated
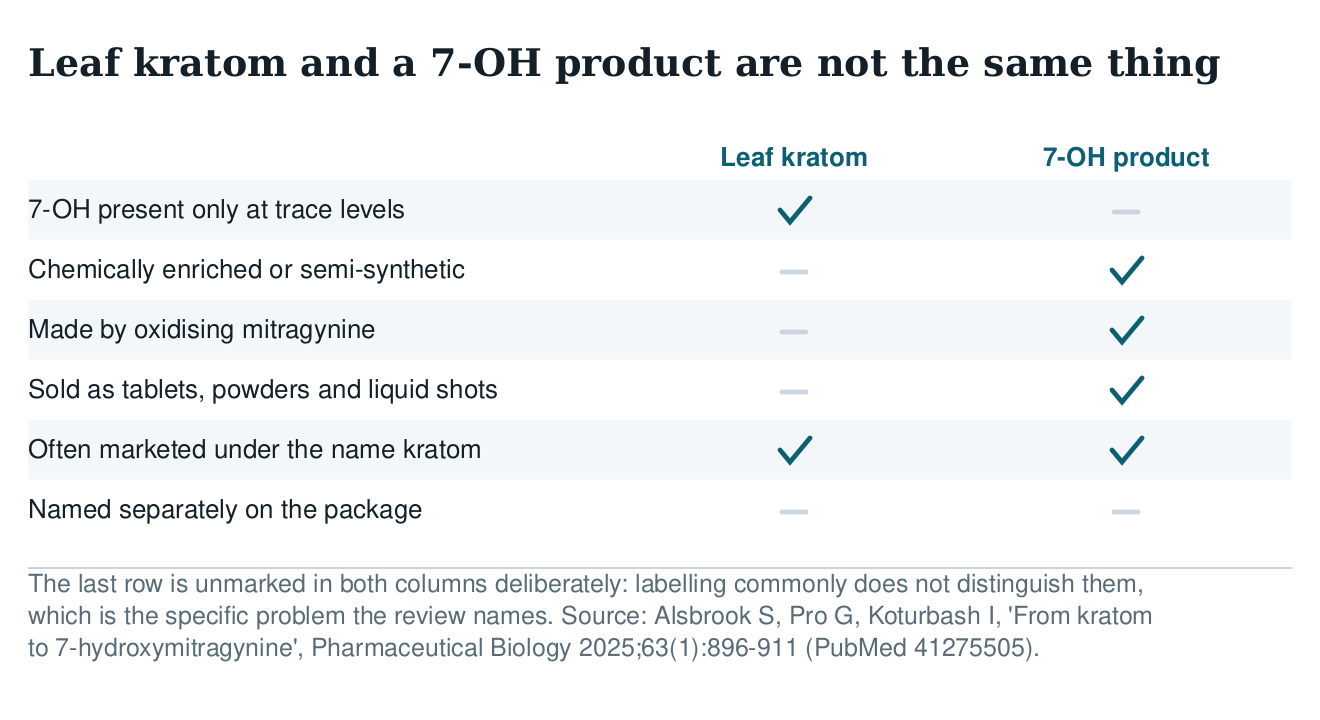
Start with the part the packaging obscures. 7-OH, short for 7-hydroxymitragynine, occurs in kratom leaf only at trace levels; the tablets, powders and liquid shots sold under that name are chemically enriched or semi-synthetic products made by oxidising mitragynine, kratom’s main alkaloid. A 2025 review in Pharmaceutical Biology describes 7-OH as a partial mu-opioid receptor agonist with nanomolar affinity whose potency often exceeds morphine, producing tolerance, dependence and reinforcing effects characteristic of opioids in animal studies. That is why withdrawal from it behaves like opioid withdrawal rather than like stopping a herbal supplement, and why people who expected the latter are blindsided by the former.
The short version
- It is not leaf kratom — 7-OH is present in the leaf only in trace amounts. The products sold are enriched or semi-synthetic, made by oxidising mitragynine
- Potency often exceeds morphine — a 2025 peer-reviewed review describes it as a partial mu-opioid agonist with nanomolar affinity and greater efficacy than mitragynine
- Dependence forms fast — a 2025 case report in the Journal of Addiction Medicine documents withdrawal after four days of use at 20 mg three times daily
- Three related substances are already Schedule I — a DEA temporary order took effect on 26 August 2026 for mitragynine pseudoindoxyl, MGM-15 and MGM-16. 7-OH itself is at an earlier stage
- The treatment directory has no category for it — we scanned the federal locator: 31 categories, 224 service values, 11,505 facilities, and zero mentions of kratom or 7-OH




The federal treatment directory has no word for it
Our analysisWe pulled the entire SAMHSA locator and read its service vocabulary end to end, because the practical question behind this page is where a person actually goes. Across 11,505 facilities the vocabulary runs to 224 values in 31 categories, and none of them names this substance.
- 0
- mentions of kratom in the vocabulary
- across 224 service values in 31 categories, pulled 29 September 2026
- 0
- mentions of 7-OH or mitragynine
- nor any catch-all such as "other substance". You cannot search for it because the category does not exist
- 5
- substances detox is recorded for
- alcohol, benzodiazepines, cocaine, methamphetamine, opioids. Kratom and 7-OH are not among them
- 53.7%
- prescribe buprenorphine
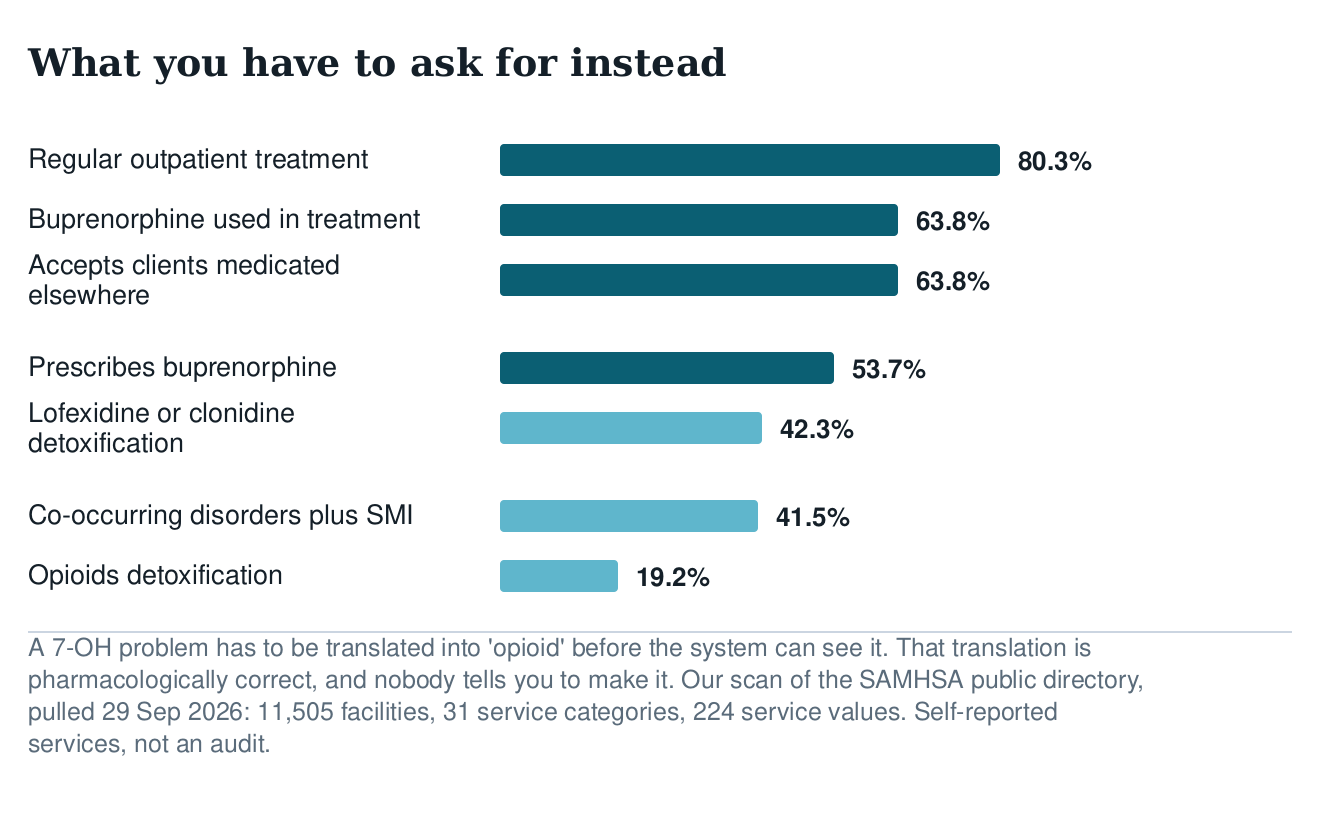
- 6,183 facilities. This is the route a 7-OH problem has to be translated into before the system can see it
- 63.8%
- accept clients medicated elsewhere
- 7,337 facilities, which matters when the prescriber and the counselling are in different places
- 42.3%
- offer lofexidine or clonidine detox
- the non-opioid medicines aimed at withdrawal symptoms, which many people are never told exist
How we got this: we pulled the full public listing from SAMHSA’s FindTreatment.gov on , removed duplicate entries by name, street and ZIP, and counted how many of the 10,233 remaining facilities report each service. SAMHSA publishes the directory; it does not publish these proportions — see how the count is made. Repeat the pull and you will get the same numbers, give or take facilities that opened or closed since.
What these numbers cannot tell you: they are self-reported by facilities, they describe availability rather than quality, and a national proportion says nothing about what is open near you this week. Use them to know what to ask for, not to decide where to go.
What 7-OH actually is
The confusion is built into how these products are sold. 7-hydroxymitragynine is a real kratom alkaloid, and the federal research institute notes that the body also produces it from mitragynine after someone swallows kratom. But a 2025 review from the University of Arkansas for Medical Sciences draws the line clearly: in traditional use, fresh leaves or teas, exposure to 7-OH is minimal because it occurs only at trace levels in the leaf. The US market offers something different, chemically enriched or semi-synthetic 7-OH products, often marketed as kratom yet chemically distinct from botanical preparations.
How the products are actually made
A case report published in the Journal of Addiction Medicine in October 2025 states it plainly: novel semi-synthetic 7-OH products are manufactured by mono-oxidation of kratom’s primary alkaloid, mitragynine. The formulations named are sublingual tablets, powders and liquid shots. So a tablet that dissolves under the tongue and a bag of leaf powder are not two strengths of the same thing. One is a plant preparation; the other is a chemically modified opioid agonist sold beside it on the same shelf.
Why the label rarely tells you
Products are commonly marketed as kratom regardless of what is in them, which is the specific problem the 2025 review names. If you are reading this because withdrawal surprised you, the mismatch between what the package implied and what your receptors experienced is not your misunderstanding. It is a labelling practice.
Why it causes dependence and withdrawal
The pharmacology is not ambiguous, and it is the reason everything else on this page follows. The federal research institute states that mitragynine and 7-OH both activate mu-opioid receptors. The 2025 review goes further on 7-OH specifically: pharmacological studies consistently identify it as a partial mu-opioid receptor agonist with nanomolar affinity, greater efficacy than mitragynine, and potency often exceeding that of morphine. Animal experiments demonstrate antinociception, respiratory depression, tolerance, dependence and reinforcing properties characteristic of opioids.
Comparisons with morphine and oxycodone
People search for these comparisons constantly and deserve a straight answer rather than a number invented for the occasion. The peer-reviewed description is that 7-OH binds with nanomolar affinity and often exceeds morphine in potency; the case report describes binding affinity greater than morphine. What nobody can give you is a clean conversion factor between a milligram of 7-OH and a milligram of anything else, because that depends on the product, the route and the person. Treat any page offering such a table as more confident than the science.
How quickly dependence forms
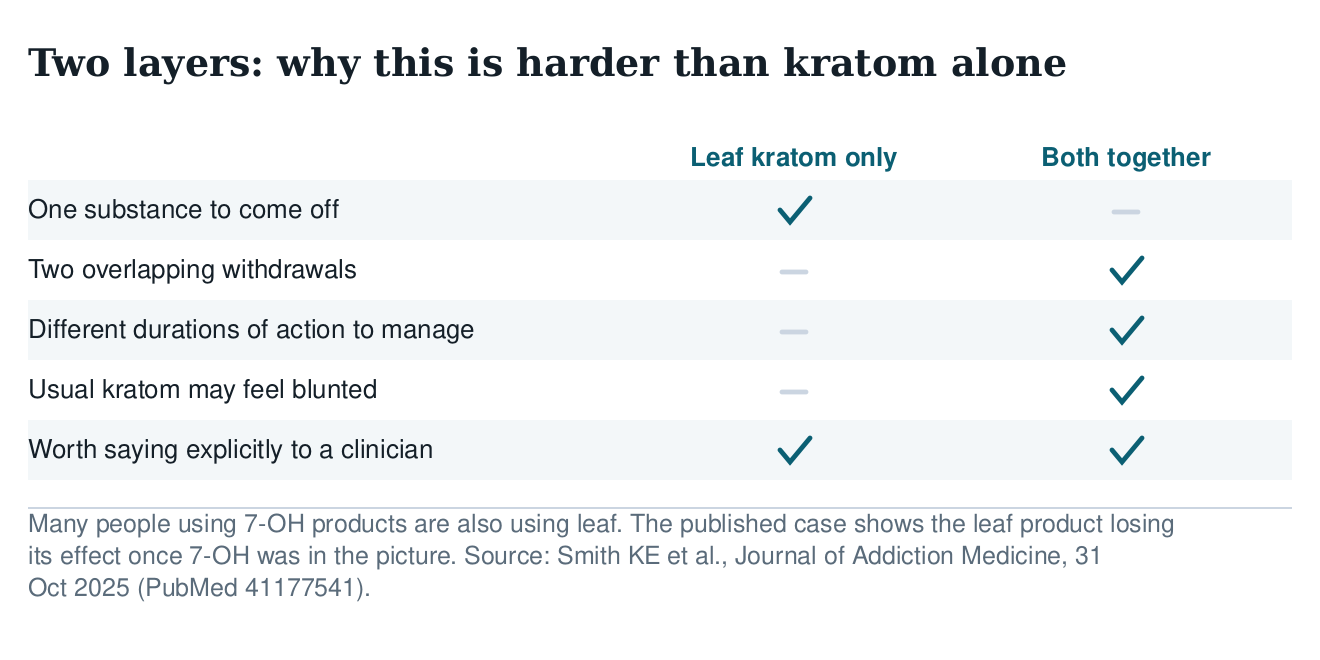
Faster than most people expect, and the published case is instructive. A 23-year-old who had used kratom for three years, about 1.5 to 2 grams of whole-leaf powder six times a day, started a semi-synthetic 7-OH product at 20 milligrams three times daily. After four days he reported withdrawal symptoms, and the effects of his usual kratom had become blunted. Four days is not a long experiment with a supplement. It is a short one with an opioid.
Route of use changes the shape of it
Sublingual tablets, swallowed powder and liquid shots do not deliver the same curve, and people also report snorting these products. Anything that raises the peak and shortens the interval tends to build tolerance faster and make the gaps between doses feel sharper. How long 7-OH takes to kick in differs by route as well, which is part of why people drift toward the faster ones. The practical marker is not which route you use but whether you have started taking it to feel normal rather than to feel anything.
The withdrawal timeline
Here is the honest framing before any numbers. There is no published, measured timeline for 7-OH withdrawal specifically, in the way there is for methamphetamine or alcohol. What exists is opioid withdrawal as a well-described syndrome, the pharmacological fact that 7-OH is a mu-opioid agonist, and accumulating clinical reports. So the shape below is the opioid shape, applied to a short-acting agonist, and it should be read as a pattern rather than a schedule.
Onset: sooner than with longer-acting opioids
People taking these products several times a day are often already experiencing early withdrawal between doses, which is one reason dosing intervals shrink over time. After a final dose, symptoms generally begin within hours rather than days. That is the opposite of buprenorphine, where a long half-life delays onset for days, and it catches out anyone who transferred expectations from one to the other.
The acute stretch
The first days are typically the worst: restlessness, sweating and chills, stomach cramps and diarrhoea, aching muscles, a running nose, yawning, dilated pupils, and sleep that refuses to arrive. Anxiety and craving run through all of it. For short-acting opioids this acute phase is usually measured in days rather than weeks, with intensity falling after the early peak.
The tail that follows
Sleep, mood and energy commonly lag behind the physical symptoms by weeks. The federal source notes that after the acute phase of kratom-related withdrawal, low mood and craving can persist. This is the stretch during which people most often conclude that stopping has not worked, and it is precisely when it is working; the warning signs worth knowing belong to these weeks rather than the first days.
Why we do not publish an hour-by-hour chart
Because the measurement that would justify one has not been done for this substance. Charts circulating for 7-OH are extrapolated from general opioid withdrawal and presented as specific. We would rather tell you the shape is reliable and the clock is not.
The two-layer problem
Many people using 7-OH products are also using leaf kratom, and the case report above shows what that does: the participant’s usual kratom produced blunted effects once 7-OH was in the picture. Stopping both at once means two overlapping withdrawals from substances with different durations, and it is a large part of why people describe this as harder than kratom withdrawal alone. If that is your situation, say so explicitly to whoever is helping you. It changes the plan.
Kratom extract is a third thing again
An extract concentrates what is in the leaf; a 7-OH product adds an alkaloid the leaf barely contains. Both are stronger than plain powder, and they are not equivalent. If you do not know which you have been taking, the honest answer is that the packaging may not tell you, and that the distinction matters more for what comes next than for what has already happened.
How dangerous is it
Two separate questions get merged here, and separating them matters. Opioid withdrawal itself is not generally considered life-threatening in the way untreated alcohol or benzodiazepine withdrawal can be; the dangers are dehydration from persistent vomiting and diarrhoea, severe low mood, and the overdose risk that follows a return to use after tolerance has fallen. Overdose on the substance is a different matter, and here the federal source is specific.
Overdose and naloxone
The federal research institute notes that neither kratom leaf nor mitragynine generally appears to produce the respiratory depression characteristic of a life-threatening opioid overdose, but that in laboratory models 7-OH can cause respiratory depression that is reversed by naloxone. The 2025 review reports respiratory depression in animal experiments as well. The practical implication is uncomfortable but simple: a product sold as a herbal supplement warrants the same overdose precaution as an opioid, and naloxone is relevant.
When to get medical help
If fluids will not stay down, if mood drops to thoughts of self-harm, if breathing seems affected, or if other substances are in the picture that carry dangerous withdrawals of their own, particularly alcohol and benzodiazepines. Withdrawal from those can kill in a way opioid withdrawal on its own does not, and their presence changes which problem is urgent.
Tapering against stopping abruptly
People search for how to quit 7-OH, and the first honest answer is that quitting slowly and quitting abruptly are different events. For opioid-type dependence, a gradual reduction is generally easier to tolerate than an abrupt stop and lowers the chance of the outcome that matters most, which is returning to use at a dose your tolerance no longer supports. The practical difficulty with 7-OH is that the products are not dosed for tapering and their content is not always reliable, so a plan built on tablet fractions rests on an assumption about what is in the tablet.
What we will not publish, and why
A milligram-by-milligram schedule. Two of the most searched phrases around this subject ask for exactly that, and the reason to refuse is not caution for its own sake. The right pace depends on how long and how much you have used, what else is involved, and how previous attempts went, and none of that is knowable from a web page. A schedule that looks authoritative invites people to follow it instead of someone who knows those things.
What to arrange instead
Somebody who knows what you are doing. Permission to slow down without treating it as failure. Naloxone in the house. Fluids and simple food within reach. And a decision made in advance about what would make you call for help, because the judgement about whether things are bad enough is exactly what the worst days impair.
Can buprenorphine help, and when
This is among the most searched questions attached to 7-OH, and it has a real answer with a real caveat. Buprenorphine is approved for opioid use disorder, and 7-OH is a mu-opioid agonist, so the question is pharmacologically sensible rather than far-fetched. But the federal research institute states that there are currently no approved medical therapies for withdrawal or substance use disorder symptoms related to kratom, and that only very limited case-level reports exist, with robust clinical trials still needed. Anyone presenting buprenorphine for 7-OH as established treatment is ahead of the evidence.
Timing is the part that can go badly wrong
Taking buprenorphine too soon after a full or strong agonist can trigger precipitated withdrawal, which is sudden and severe rather than gradual. The FDA prescribing information for buprenorphine with naloxone instructs that induction be undertaken only when objective and clear signs of withdrawal are evident, and in divided doses; we cover that label in detail on Suboxone withdrawal timeline. That instruction exists because getting the timing wrong produces an experience far worse than waiting would have been.
Taking 7-OH while on buprenorphine, or after it
Searches ask this in both directions. Buprenorphine binds mu-opioid receptors with high affinity and only partially activates them, so it both occupies the receptor and limits what another agonist can do there. Using 7-OH on top of it tends to produce less effect than expected while adding risk, and using buprenorphine on top of recent 7-OH is the precipitated-withdrawal scenario above. Neither is a home experiment; both are a conversation with the prescriber managing your care.
What else a prescriber may consider
Non-opioid medicines aimed at the autonomic symptoms exist and are recorded in the federal directory as a distinct service, the same ones we counted for stimulant withdrawal. In our count, 42.3 per cent of facilities report lofexidine or clonidine detoxification. They do not remove withdrawal and they are not a substitute for a sensible pace, but they are a real option many people are never told about.
Where to get help when the directory has no word for it
We pulled the entire federal treatment locator and read its service vocabulary end to end, because the practical question behind everything above is where a person actually goes. The result is worth stating precisely: across 11,505 facilities, 31 service categories and 224 distinct service values, the words kratom, mitragynine and 7-hydroxymitragynine do not appear once. Neither does any catch-all such as other substance. Detoxification is recorded for exactly five substances: alcohol, benzodiazepines, cocaine, methamphetamine and opioids.
| What we searched the vocabulary for | Matches |
|---|---|
| kratom | 0 |
| mitragynine | 0 |
| 7-hydroxymitragynine, 7-OH, 7oh | 0 |
| herbal, botanical | 0 |
| "other substance", "novel", "synthetic" | 0 |
| Substances detox is recorded for | alcohol, benzodiazepines, cocaine, methamphetamine, opioids |
kratom
0
mitragynine
0
7-hydroxymitragynine, 7-OH, 7oh
0
herbal, botanical
0
"other substance", "novel", "synthetic"
0
Substances detox is recorded for
alcohol, benzodiazepines, cocaine, methamphetamine, opioids
What that means in practice
It does not mean help does not exist. It means the directory gives you no way to ask for it in the words you would naturally use, so you have to translate your own situation into opioid before the system can see you. That translation is pharmacologically correct, and nobody tells you to make it. If you take one practical thing from this page, take that.
What to ask for instead
Ask for a provider who prescribes buprenorphine, which 53.7 per cent of facilities in our pull report doing, and say plainly what you have been taking, how much and for how long. Note that 63.8 per cent accept clients whose medication is prescribed elsewhere, which matters if your prescriber and your counselling end up in different places. If mental health is part of the picture, 41.5 per cent report treating co-occurring disorders alongside serious mental illness; what a programme actually consists of is on what happens in rehab.
What these numbers are not
Self-reported service categories rather than an audit of quality. They also come from a pull with a different denominator from our other pages, 11,505 against 8,848 and 9,152, because this one kept every facility with any recorded service in order to read the whole vocabulary. Use the figures for the shape of the landscape and the phone call for the specific place, and do not mix the denominators.
Is 7-OH banned? What the record actually says
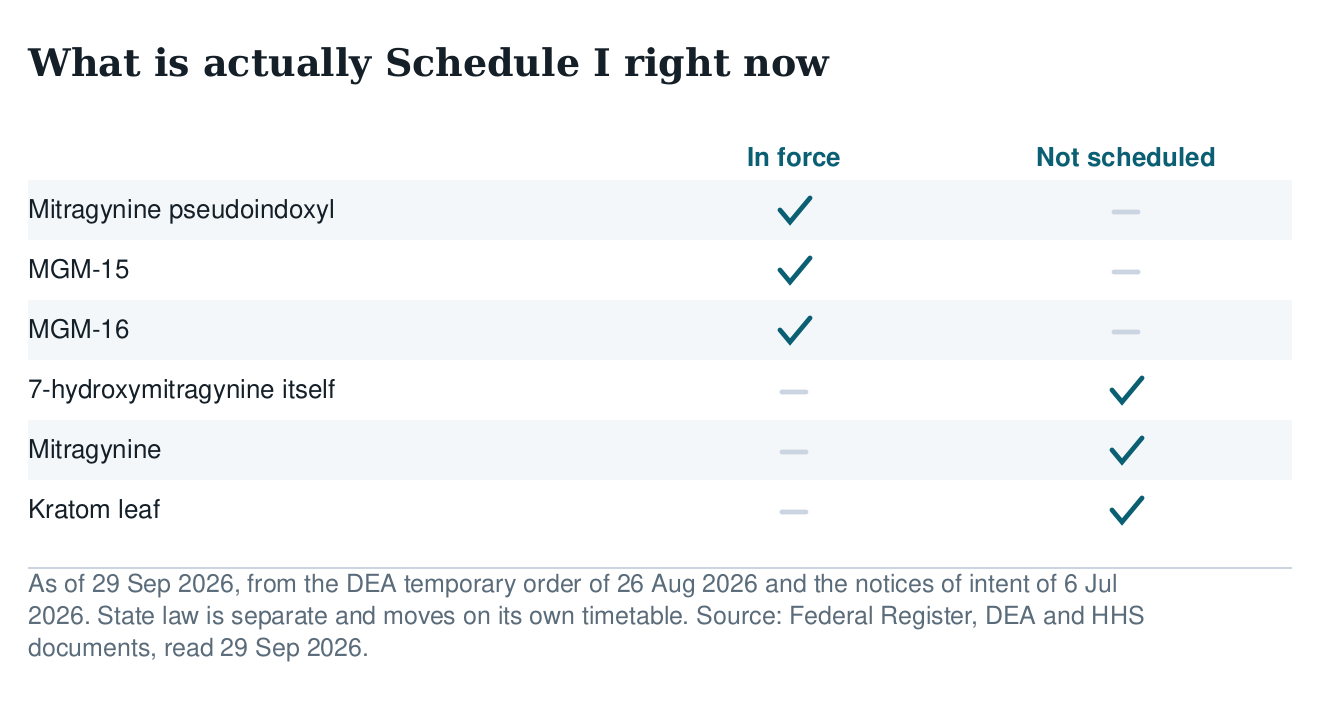
This is the question with the most search traffic attached to it and the most confusion around it, largely because people are reading news coverage rather than the documents. We read the Federal Register itself. As of 29 September 2026 the position has two halves, and conflating them is what produces the wrong answer in either direction.
Already in force
On 26 August 2026 the Drug Enforcement Administration issued a temporary scheduling order placing three 7-OH-related substances, mitragynine pseudoindoxyl, MGM-15 and MGM-16, into Schedule I of the Controlled Substances Act, along with their isomers, esters, ethers and salts. The agency based the action on a finding that doing so was necessary to avoid an imminent hazard to public safety. That order imposes the full regulatory controls and criminal sanctions that attach to Schedule I substances on anyone who manufactures, distributes, imports, exports, researches or possesses them.
Proposed but not yet in force
7-OH itself is at an earlier stage. On 6 July 2026 the DEA published a notice of intent to issue a temporary order scheduling 7-hydroxymitragynine above a specified threshold. A notice of intent is not the order. On the same day, the Office of the Assistant Secretary for Health opened a public docket seeking input on what that threshold should be, and on 26 August 2026 it extended the comment period in response to a request for more time. So the threshold that would define which products are covered was still under public consultation as this page was written.
Why the words "above a specified threshold" matter
They are the whole mechanism. Leaf kratom contains trace 7-OH, and the body makes 7-OH from mitragynine after any kratom is swallowed. A ban written without a threshold would sweep in the plant itself. A threshold aims the rule at concentrated and semi-synthetic products while leaving leaf preparations outside it. That is why the number is being argued over publicly rather than simply announced.
There is precedent for this not finishing
In August 2016 the DEA published a notice of intent to place mitragynine and 7-OH into Schedule I temporarily. In October 2016 it published a withdrawal of that notice of intent. Ten years later the agency is back, with a narrower target and a threshold. Anyone telling you confidently what will happen next is guessing; the 2016 file is the reason to be careful about that.
Mitragynine pseudoindoxyl, MGM-15 and MGM-16
These names appear in the DEA order and almost nowhere else that a general reader would encounter, which is why searches for them are rising. Searches for mgm15 vs 7oh are rising for a reason: they are 7-OH-related substances, distinct compounds rather than alternative names for 7-OH, and they are the three that are actually in Schedule I as of 26 August 2026. If a product lists one of them, its legal position is not the same as a 7-OH product, and neither is it the same as leaf kratom.
What the order covers and what it does not
It covers those three substances including their isomers, esters, ethers, salts, and salts of those, wherever such forms are possible. It does not, by itself, schedule 7-OH. It does not schedule mitragynine or kratom leaf. Reading a headline about a kratom ban and concluding that everything is now illegal is the mistake the document itself does not support.
State law, and why we do not print a table
Several states have acted on kratom and 7-OH on their own timetable, and searches for individual states are among the most common around this subject. We are not publishing a state-by-state table, and the reason is the same one that applies to a dosing schedule: a table that looks authoritative and is three months stale is worse than no table, and legal status here is moving month to month while the federal threshold is still in consultation.
How to check your own state reliably
Look for your state legislature’s own bill tracker or your state health department, rather than a vendor’s legality map, since vendors have an interest in the answer. Search for the substance by both names, kratom and 7-hydroxymitragynine, because statutes often name one and not the other. And check the date on whatever you find before you rely on it.
Does 7-OH show up on a drug test
Usually not on a standard panel, and that surprises people in both directions. Routine workplace panels look for a defined list of substances, and kratom alkaloids are generally not among them. Specific testing for mitragynine and its metabolites does exist and is used in clinical and forensic settings, so the accurate statement is that it is not normally tested for rather than that it cannot be detected.
Why this is a different question from withdrawal
Detection windows describe what a laboratory can measure, the way our page on how long Suboxone stays in your system sets out for a different drug. Withdrawal describes what happens once concentrations fall below what your nervous system has adapted to. The two are connected by the same pharmacokinetics, which is why they get confused, and knowing a detection window tells you nothing useful about how the next week will feel.
Why so much of this comes from forums
Search results for 7-OH fill up with Reddit threads, and searches for quitting 7oh on Reddit outnumber most clinical queries on the subject. The volume of those searches is itself a finding: people are getting their information from each other because there is little else. That is not a criticism of the forums, which are often the only place where the specific products and their effects are discussed at all. It is a reason to read them with the selection effect in mind.
How to read personal accounts
People for whom stopping went smoothly rarely post about it. Accounts cluster at the hard end, and they rarely say what product, what dose or what else was involved, which are the three things that most change the experience. Use them for recognition, that what you are feeling is a known thing rather than something wrong with you, and use a clinician for the plan.
What this page cannot tell you
It cannot give you an hour-by-hour timeline, because that measurement has not been made for this substance and the charts circulating are opioid withdrawal in borrowed clothes. It cannot give you a taper schedule or a dose equivalence, for reasons stated above rather than hidden. It cannot tell you your state’s law today with confidence. What it can do is tell you exactly what 7-OH is, what the peer-reviewed pharmacology says about its potency, what the Federal Register record actually contains as of today, and the uncomfortable fact that the country’s main treatment directory has no word for the thing you are trying to stop.



Where this sits in the system of care
Addiction treatment is organised into levels of care, and clinicians choose between them using the ASAM criteria (six dimensions covering withdrawal risk, medical and psychiatric conditions, readiness, relapse risk and, decisively, the environment you return to. Facilities are licensed by the state and many hold additional accreditation from bodies such as the Joint Commission or CARF; that status is worth confirming for any specific programme. Percentages below are our count of how many facilities in the federal directory report offering each level of care.
- Detox19.5% of facilitiesmedical withdrawal management, 3–7 daysDetox vs rehab
- Residential21.4% of facilitieslive on site, 24-hour staffingInpatient vs outpatient
- PHP20–30 structured hours a week, sleep at homePHP vs IOP
- IOP9–19 hours a week, usually compatible with workPHP vs IOP
- Standard outpatient85.4% of facilities1–8 hours a week, the maintenance levelMutual aid options
“Remaining in treatment for an adequate period of time is critical.”
Programmes for specific groups
Facilities also report dedicated programming, and the coverage is wider than most people expect, worth asking about before assuming a programme will not fit. From our count: 42.7% run programmes for adolescents, 39.2% for veterans, 38% for pregnant and postpartum women, and 25% provide services in Spanish. Medication for opioid use disorder is available at 59.2% (buprenorphine) and 13.7% (methadone).
Cost and coverage vary by level: residential care is the tier insurers scrutinise most and almost always requires prior authorisation before admission. See what your plan covers and how to pay without insurance. Family involvement is a standard part of most programmes, and aftercare planning ( step-down to a lower level, sober living, relapse prevention) should be discussed before admission, not at discharge. If a mental health condition is also present, ask specifically whether the programme is staffed for co-occurring disorders: 69.5% of facilities in the directory report treating them, but that is a self-reported field worth confirming.



Common questions
What is 7-OH?
7-hydroxymitragynine, an alkaloid present in kratom leaf only at trace levels and also produced in the body from mitragynine. The tablets, powders and liquid shots sold under the name are chemically enriched or semi-synthetic products made by oxidising mitragynine, which a 2025 review in Pharmaceutical Biology describes as chemically distinct from botanical kratom preparations.
How long does 7-OH withdrawal last?
There is no published measured timeline for 7-OH specifically. It behaves as short-acting opioid withdrawal: onset generally within hours of the last dose, an acute stretch measured in days with the worst early, and a tail of disturbed sleep, low mood and craving that can run for weeks. Anyone giving you an hour-by-hour chart is extrapolating and not saying so.
Is 7-OH stronger than morphine?
A 2025 peer-reviewed review describes 7-OH as a partial mu-opioid receptor agonist with nanomolar affinity, greater efficacy than mitragynine, and potency often exceeding that of morphine. A 2025 case report describes binding affinity greater than morphine. What does not exist is a reliable milligram-for-milligram conversion, because that depends on the product, the route and the person.
Is 7-OH banned?
Partly, and the halves matter. A DEA temporary order effective 26 August 2026 placed three related substances, mitragynine pseudoindoxyl, MGM-15 and MGM-16, into Schedule I on a finding of imminent hazard to public safety. 7-OH itself was still at the notice-of-intent stage, with the threshold that would define coverage out for public comment, the period extended on 26 August 2026.
When does the 7-OH ban start?
For the three related substances it already has, since 26 August 2026. For 7-OH above a threshold there is no date: the DEA published a notice of intent on 6 July 2026, and a notice of intent is not the order. The threshold itself was still under public consultation as this page was written.
How fast does dependence on 7-OH develop?
Faster than people expect. A case report in the Journal of Addiction Medicine documents a participant who started a semi-synthetic 7-OH product at 20 mg three times daily and reported withdrawal symptoms after four days, with the effects of his usual kratom blunted.
Does Suboxone help with 7-OH withdrawal?
The question is pharmacologically reasonable, since 7-OH is a mu-opioid agonist. But the federal research institute states there are currently no approved medical therapies for kratom-related withdrawal, with only limited case-level reports. Timing also matters: the FDA label instructs that buprenorphine induction begin only when objective and clear signs of withdrawal are evident, because starting too soon can precipitate severe withdrawal.
Can you take 7-OH while on Suboxone?
Buprenorphine occupies mu-opioid receptors with high affinity and only partially activates them, so another agonist on top tends to produce less effect than expected while adding risk. Taking buprenorphine shortly after 7-OH is the precipitated-withdrawal scenario, which is sudden and severe. Both directions are a prescriber conversation, not a home experiment.
Can you overdose on 7-OH?
The federal research institute notes that while kratom leaf and mitragynine generally do not appear to cause the respiratory depression characteristic of a life-threatening opioid overdose, 7-OH can cause respiratory depression in laboratory models, reversed by naloxone. A 2025 review reports the same in animal experiments. Naloxone is relevant to a product sold as a supplement.
Does 7-OH show up on a drug test?
Not usually on a standard workplace panel, which looks for a defined list that generally does not include kratom alkaloids. Specific testing for mitragynine and its metabolites exists in clinical and forensic settings, so it is not normally tested for rather than undetectable.
Where can I get treatment for 7-OH?
Through the opioid route, and you will have to make that translation yourself. We scanned the federal treatment directory: 11,505 facilities, 31 categories, 224 service values, and no mention of kratom or 7-OH anywhere. Ask for a provider who prescribes buprenorphine, reported by 53.7% of facilities, and describe plainly what you have been taking.
What is the difference between 7-OH and kratom extract?
An extract concentrates what is already in the leaf. A 7-OH product adds an alkaloid the leaf barely contains, made by oxidising mitragynine. Both are stronger than plain leaf powder and they are not equivalent, and the packaging often does not make clear which one you have.
Sources
- Alsbrook S, Pro G, Koturbash I. "From kratom to 7-hydroxymitragynine: evolution of a natural remedy into a public-health threat", Pharmaceutical Biology 2025;63(1):896-911 (PubMed 41275505)
- Smith KE et al. "Complicating Factors Surrounding Concurrent Use of Kratom and a Novel 7-hydroxymitragynine Product", Journal of Addiction Medicine, 31 Oct 2025 (PubMed 41177541)
- NIDA: Kratom, on mitragynine and 7-OH at mu-opioid receptors, naloxone-reversible respiratory depression in laboratory models, and the absence of approved therapies
- DEA temporary scheduling order for mitragynine pseudoindoxyl, MGM-15 and MGM-16, Federal Register, 26 August 2026 (document 2026-17429)
- DEA notice of intent: temporary placement of 7-hydroxymitragynine above a specified threshold in Schedule I, Federal Register, 6 July 2026 (document 2026-13580)
- HHS request for information on the 7-OH threshold, Federal Register, 6 July 2026 (document 2026-13608)
- SAMHSA FindTreatment.gov, the public directory whose service vocabulary we scanned
Compare levels of care
Check what your plan covers
How this page was made
- Who wrote it:
- the Treatment Compass editorial team : researchers and writers, not clinicians. No doctor has reviewed this page, and we do not claim otherwise. What that means in practice: we report what public clinical sources say and show you where to read them, rather than offering a clinical opinion of our own.
- Checked against:
- 7 primary sources listed above: federal agency material and published clinical criteria. Where a figure varies by state, plan or facility, we say so instead of publishing a number that looks authoritative and is not.
- Original analysis:
- the facility proportions on this page are our own count of SAMHSA’s public directory. The full method is documented , including what we count, what we deliberately do not publish, and an error the approach caught. You can repeat the pull and check the numbers.
- Last reviewed:
- . This date changes when the content is actually re-checked, not automatically on every visit.
- What this page is not:
- a medical recommendation, a diagnosis, or a referral. Decisions about levels of care and medication belong with a clinician who knows your history. We do not operate facilities, take placement fees, or receive payment for sending anyone anywhere.
Related on this site
- Suboxone withdrawal timelinethe other side of the buprenorphine question, including what the label says about induction
- Opioid withdrawal timelinethe syndrome this one follows, described where it has actually been measured
- How long Suboxone stays in your systemdetection windows and pharmacokinetics, the question people confuse with withdrawal
- Relapse warning signsthe weeks after the acute phase, when the tail is easiest to misread
More guides
- How to Get Someone Into RehabYou usually cannot force an adult into addiction treatment. What works is removing the obstacles, picking the moment, and knowing the legal exceptions.
- Paying for Rehab Without InsuranceState-funded programmes, sliding-scale fees, federal block grants and payment plans. What each option actually is, who qualifies, and how to reach it.
- Rehab Rules: What You Can and Cannot Do in TreatmentWhat treatment facilities restrict and why: phones, visitors, relationships, leaving early. Rules vary by level of care, so here is what to ask first.
- Suboxone Withdrawal Timeline: Why It Starts Late and Lasts LongerWhy buprenorphine withdrawal is delayed, what the FDA label says about tapering, and our count of how many US facilities will actually help you come off.
- Meth Withdrawal Timeline: What the Evidence Actually SaysWhere the 7-to-10-day figure comes from, why NIDA and the original study disagree, and our count of how few US facilities offer stimulant detox.
- Cocaine Withdrawal Timeline: What the Days Actually Look LikeThe crash, the weeks after, and why the withdrawal is not the dangerous part. With our own count of which treatments US facilities actually offer.
- Opioid Withdrawal Timeline: What Happens, and WhenSymptoms start around 12 hours after short-acting opioids and 30 after methadone. Fentanyl changes the picture, and the real danger comes after it ends.
- Relapse Warning Signs: What Comes Before Using AgainRelapse starts weeks before anyone picks anything up. The published model names three stages, and the early one has no thoughts of using in it at all.
- Rehab for Professionals: What Is Actually DifferentLicensed professionals get the best documented outcomes, and the most monitoring. What that trade involves, state by state.
- What Happens in Rehab: The Day, the Week, the MonthAdmission day is paperwork, not therapy. Most of the rest is group work. An honest account of the schedule, the therapies by name and the emotional arc.
- Court-Ordered Rehab: How It Works and What the Evidence ShowsA judge can order treatment by several routes, each with different consequences. Drug court, civil commitment and what each means.
- Sober Living Rules: What They Are and What Is EnforceableAbstinence, testing, curfew, chores and rent are near-universal. What is negotiable, what the law protects, how to spot a bad house.
- How Long Does Suboxone Stay in Your System?Buprenorphine has a 24 to 42 hour half-life. Urine tests find it for about a week, hair for months, and the blocking effect fades sooner than the drug does.
Weighing levels of care? See PHP vs IOP and what your insurance covers.
This page is information, not medical or legal advice. Laws on commitment and treatment differ by state. If you are in crisis, call or text 988 in the US, or reach the SAMHSA National Helpline at 1-800-662-4357 — free, confidential, 24/7.